Felipe Rios Mendoza’s right arm fell limp, the phone in his hand slipping to the floor. Frightened family members rushed him to the hospital near their home outside Panama City, where diagnostic imaging confirmed a blockage in a major artery of the brain.
Neurosurgeon Vitor Mendes Pereira was at Hospital Medica Norte in Santiago, Panama, when he got the call. Rios Mendoza was a candidate for an experimental procedure that the doctor, his colleagues and robot developer XCath had spent years preparing for: the world’s first telerobotic neurosurgery.
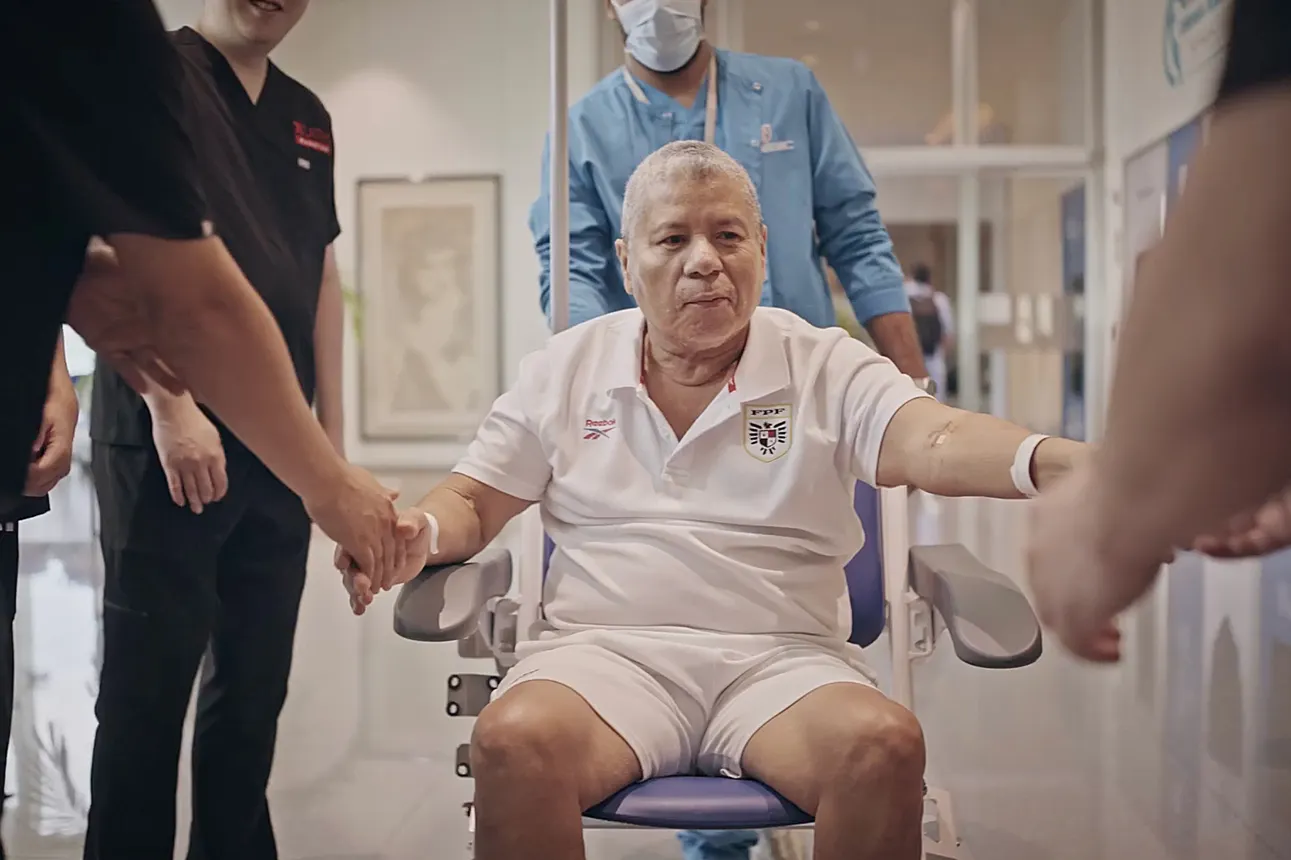
Transferred to a clinic some 150 miles from Hospital Medica Norte, Rios Mendoza was diagnosed with a severe form of ischemic stroke. The 68-year-old’s survival depended on rapid intervention to remove the blood clot. Sitting at the controls of XCath’s system in Santiago that March day, Pereira performed a telerobotic mechanical thrombectomy, assisted by clinicians at the patient’s bedside. The procedure was a success.
“This patient was very much on the most extreme end of what we thought we could manage,” recalled XCath CEO Eduardo Fonseca. Yet two hours later, Rios Mendoza was talking and moving again. “It is the best-case scenario,” said Fonseca.
Remote stroke treatment illustrates the promise of telesurgery to reach people who lack timely access to the level of care that can save lives or prevent disability. A growing number of physicians, medtech companies and government agencies see the potential to expand access to emergency and specialized care in communities facing surgeon shortages, both in the U.S. and globally.
Heart surgery in India, hysterectomy in Kuwait and lung surgery in Brazil are some of the procedures that remote robots have already enabled.
“I think telesurgery will fundamentally change the way we look at surgical care of patients and education of surgeons,” said Vipul Patel, a urologist who in June 2025 completed a transatlantic prostatectomy, operating from Florida on a cancer patient nearly 7,000 miles away in Luanda, Angola.
“The reason is, it is so much easier if you are able to operate or teach remotely from one location to another,” said Patel. “That has huge implications in terms of underserved areas of the world.” Neurosurgical care, in particular, is inaccessible to more than two-thirds of the global population.
Over half of Americans live more than an hour from a stroke center capable of providing thrombectomy, according to the Advanced Research Projects Agency for Health, known as ARPA-H. The U.S. agency last month awarded up to $175.3 million to a group of universities and companies, including Siemens Healthineers and Philips, to develop robots for long-distance thrombectomy procedures.
“Stroke is the biggest need in healthcare because the deficits and the consequences are astronomical,” said Patel, who is medical director of AdventHealth’s Global Robotics Institute in Celebration, Florida, and executive director of the Society of Robotic Surgery, an organization promoting international collaboration to advance the technology.
Early days for telesurgery
While robotic surgery has entered the mainstream — pioneer Intuitive’s systems have supported more than 20 million surgeries since the company’s founding three decades ago — telerobotic surgery remains in its infancy. Patel estimates that roughly 5,000 remote surgeries have been performed around the world to date.
Telesurgery cases are increasing now because robotics technology and communications networks have improved since the groundbreaking Lindbergh Operation in 2001, where surgeons in New York City performed a gallbladder removal on a patient in Strasbourg, France. Patel’s intercontinental surgery relied on high-speed data transmission along 10,000 miles of direct fiber optic cables running from Orlando to Miami to Brazil to Angola.

In the U.S., no surgical robots are currently authorized for remote procedures. China and India are leading the way in telesurgery, with systems built by domestic manufacturers. MicroPort MedBot’s Toumai’s platform has been used in many global procedures, including Patel’s Florida-to-Angola operation. The surgery was conducted under an investigational device exemption approved by the Food and Drug Administration.
In June, Shanghai-based MicroPort gained CE mark certification in Europe for robot-assisted telesurgical procedures in urology, general surgery, thoracic surgery and gynecology.
India’s SS Innovations International, founded by heart surgeon Sudhir Srivastava, designed its SSi Mantra system to incorporate both teleproctoring for surgeons to share expertise and telesurgery to reduce the travel burden on patients. Srivastava, the CEO, argues that robotic surgery is by definition a teleoperation, because the surgeon works from a console away from the patient, controlling the instruments in the body cavity through the robot’s arms.
In both robotic and telerobotic surgery, the system must respond precisely.
“There will always be some delay, just because of the digital processing, whether it is the video processing or the hand signal processing,” said Srivastava. “So now the question is, how far can you go where you're away from the patient?”
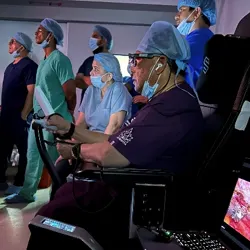
SS Innovations gained expanded approval in India for teleproctoring and telesurgery in November 2024. More than 185 robotic telesurgeries have been performed with the SSi Mantra system, including more than 25 cardiac telesurgeries, according to the company. SS Innovations is also approved for telesurgery in Indonesia and the Philippines.
The FDA is closely watching the progress of companies developing telesurgery capabilities. Robotically assisted surgical devices appear on the latest "Under Construction" list of proposed guidance documents the regulator intends to develop.
“The agency is committed to advancing innovation of robotic medical devices, including robotically assisted surgical devices and endoluminal navigation devices with robotically assisted components for remote procedures,” an FDA spokesperson wrote in an email.
Earlier this month, the FDA granted breakthrough status to XCath for the Iris robot used in Rios Mendoza’s procedure. The program is designed to speed development and review of promising technologies.
Telesurgery at scale
Top medical device companies such as Medtronic, Johnson & Johnson and Intuitive, along with startups like Houston-based XCath, are laying the groundwork for a day when telerobotic surgery could become a viable option for more patients.
Intuitive said it has built the foundation through investments in remote surgical collaboration, digital connectivity, dual console surgery and connected platforms. The company’s da Vinci systems support telepresence capabilities that allow surgeons to observe and learn remotely in real time.
Intuitive is developing telesurgery technology for da Vinci 5, its latest-generation system.
“We believe the long-term value of telesurgery lies in expanding access to experience while helping healthcare systems reduce variability and improve consistency of care to support patient care across distance,” Intuitive said in an email.
Realizing telesurgery at scale will require coordinated efforts on technology, network infrastructure, data interoperability, AI-enabled decision support, regulation, reimbursement, licensing and clinical workflow integration, the company said, adding that “ultimately, trust will also play a major role in determining the pace of adoption.”
"We believe telesurgery will have a role within a connected surgical ecosystem in the future, but there is still much work to do to ensure it’s done the right way for patients, providers and payers."

James Porter
Chief medical officer for robotic surgical technologies and digital technologies at Medtronic
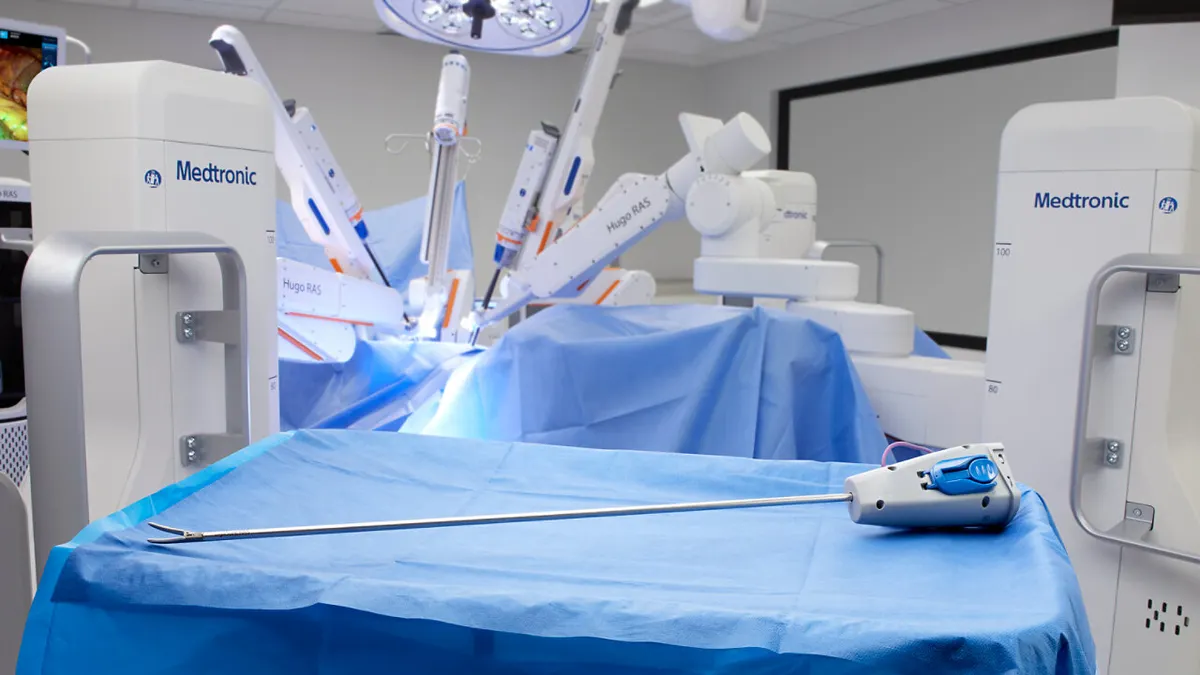
Surgeons operating Medtronic’s Hugo robot can now use telepresence to consult with colleagues via live streaming during a procedure, said George Murgatroyd, vice president and general manager of digital technologies.
“Our technology allows surgeons in an operating room, within two taps, to invite potentially any surgeon worldwide to join them in that case,” Murgatroyd said. Hugo is available in more than 35 countries globally, including the U.S.
“The basic needs of being able to connect surgeons live, to just get second opinions, to proctor, to bring trainee surgeons into the operating room without having to scrub in — that is still very minimally penetrated in operating rooms,” said Murgatroyd. “Among some surgeons, they're seeing that as likely a much bigger impact to the surgical community at scale than potentially having a surgeon 2,000 miles away jump on a robot and operate on you.”
James Porter, chief medical officer for robotic surgical technologies and digital technologies at Medtronic, said connecting surgeons remotely during surgery is already transforming the culture of education and training and fueling borderless collaboration.
“We believe telesurgery will have a role within a connected surgical ecosystem in the future, but there is still much work to do to ensure it’s done the right way for patients, providers and payers,” Porter said.
J&J, whose Ottava surgical robot received FDA authorization in July, said its strategy begins with secure intraoperative telepresence capabilities offered today to enable real-time collaboration beyond the operating room. From there, it will scale toward remote surgery as clinical, regulatory and economic conditions allow.
“Looking ahead, we believe telesurgery has the potential to redefine how surgical expertise is delivered,” a J&J spokesperson said.
Challenges to expansion
Binita Ashar, a former FDA office director who oversaw a team focused on robotic surgery technologies, said challenges such as credentialing in the hospital, licensure across states and reimbursement considerations are hurdles in the path to wider telesurgery adoption.

“There are a lot of areas that need to be discussed to be able to understand what readiness is,” said Ashar, “so that when you do deploy something, you're confident about how everyone will function.”
Having a feasible backup plan for handling dropped signals or latency problems will also be important, said Ashar, founder of Clarity Surgical Advisors and research professor of surgical sciences at Western Michigan University Homer Stryker M.D. School of Medicine.
“The technology, the robot, is the part that I'm least worried about,” Ashar said.
Mischa Dohler, vice president for emerging technologies at networking and telecommunications company Ericsson, said networks five to 10 years ago weren’t up to the task, but “today, we have networks which are extraordinarily reliable.”
Fiber optics can now be backed up with 5G wireless networks to give hospitals redundancy in their systems. “We can ensure that during the operation, when one link goes down, the operation doesn't become life threatening, and that's what the FDA also wants,” Dohler said.
Ultimately, telesurgery benefits patients by reducing the expense, uncertainty and trauma that comes with traveling long distances to receive advanced medical care, said SS Innovations’ Srivastava. “This problem of rural populations exists everywhere in the world,” he said. “That’s the reality.”
Building trust so patients understand they will get the same care from a surgeon operating remotely will be a process, he acknowledged.
“Now, it may take a little time,” said Srivastava. “Psychologically, people are used to having a surgeon in the operating room. We have already shown it can be done.”